I-site newsletter is a global educational newsletter launched in 2009, that monthly provides independent updates from the international literature on specialty (R)GP lenses such as corneal, orthokeratology and scleral lenses and related topics. View as Webpage
|
|
After the tsunami of scleral lens publications in the latter part of 2020 (see I-site newsletter November and December 2020), it is time to digest all of that and to reflect. Maybe this new study from the Kellogg Eye Center at the University of Michigan (US) sums it all up: The impact of scleral lens use on the rate of corneal transplantation for keratoconus. The study supports clinical evidence from corneal experts that patients’ access to scleral lenses reduces the risk of keratoplasty for patients with keratoconus. Scleral lenses can indeed delay and/or prevent corneal surgery in keratonus patients, with huge ecomonic and lifestyle benefits. Physicians should maximize the use of scleral or corneal GP lenses because patients who successfully use contact lenses have almost one-fifth the risk of undergoing keratoplasty. What a great way to start 2021. I-site newsletter started early last year with 'Hindsight is 20/20'. Let's not look back to last year too much. Happy new year to everyone, and off to new beginnings!
Eef van der Worp
|
|
After the scleral lens turmoil of last year, it is good to see that corneal lenses do get their fair share of attention too. In Contact Lens Spectrum a number of interesting articles refer to various aspects of corneal lens fitting. |
|
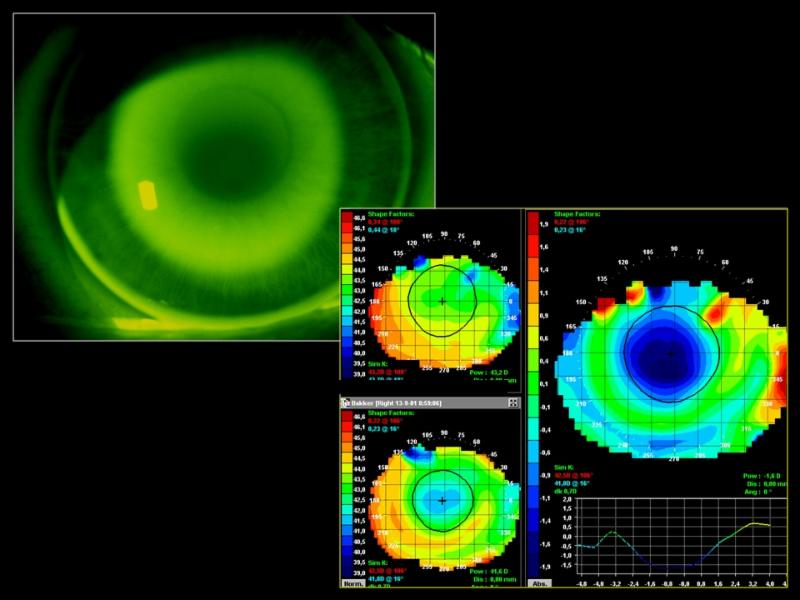
There is a growing resurgence of interest in corneal lenses, write Annie Chang and Timothy Edrington - due to myopia management but also because corneal lenses are being used to manage patients who have irregular corneas when reduced cost and ease of handling are desired. In their Spectrum article, they explain how to indentify four types of corneas based on fluorescein pattern evaluation. If patients are not correctable to 20/20 with manifest refraction and have large amounts of refractive astigmatism, confirming the type of cornea is helpful in determining the lens design and parameters. They identify 1) the 'Significantly Toric Regular Cornea,' with a dark horizontal band indicating a with-the-rule pattern. A toric-back-surface corneal GP lens would improve lens centration and comfort here. Exhibit #2 shows a spherical corneal lens on a patient who has keratoconus. This patient also exhibits large amounts of corneal toricity, but unlike the previous patient, the cornea is irregular. Rather than a dark horizontal band, a small circular area represents the apex of the cone. This is a 'three-point-touch' pattern. Number 3 is a pellucid marginal degeneration (PMD). PMD and keratoconus are both corneal ectasias, but PMD differs in that the location of protrusion is peripheral; when viewing the fluorescein pattern, the area of bearing is decentered inferiorly. Because the area of highest elevation is inferior, corneal lenses tend to decenter inferiorly, which requires a larger lens. Lastly (#4), a fluorescein pattern of a post-radial keratotomy cornea is shown, with varied areas of pooling and bearing that are unique from cornea to cornea. Because of the irregular topography, a larger-diameter lens can improve centration and allow for a larger optic zone.
|
|
Do We Have Edge-Clearance? |
|
We all strive to make our corneal lens fits as comfortable as possible, writes John Mark Jackson. One of the most critical factors for corneal lens success is the edge clearance, which is essentially the gap between the back of the lens and the cornea under the peripheral curves. We indirectly measure the edge clearance when we evaluate the amount of fluorescein dye under the peripheral area of the lens. Ideally, we want an even band of dye around the lens perimeter that is roughly 0.5mm to 0.75mm wide—not too wide, not too narrow, and showing symmetry in the width of the band. Excessive edge cleareance will cause too much lid interaction and will decrease comfort or will cause the lens to position too far under the upper lid. Insufficient edge clearance, however, can cause the lens to position inferiorly and will inhibit tear exchange. Both excessive and insufficient edge clearance can cause 3 o’clock and 9 o’clock corneal staining, which can lead to vascularized limbal keratitis. One potential issue that can occur is when there is asymmetry in the amount of clearance in different meridians. Ideally, the peripheral band of fluorescein should be the same width around the entire contact lens. When it’s not, there are a few options to try, such as toric peripheral curves and asymmetric peripheral curves. |
|
There is a debate in the international community as to whether orthokeratology (OK) works as well in lower myopes for myopia control as it does in higher levels of myopia. The rationale behind this is that myopia research in general seems to indicate that higher 'near add' is needed for maximal effect. Correction of low myopia with orthokeratology may lead to relatively lower 'plus' values in the periphery. However, an editorial in myopiaprofile.com questions this assumption. In short, Kate Gifford states that there is currently no supportive evidence for OK being less effective in lower than in higher myopia. It should work similarly for myopia control regardless of baseline myopia. There is also no evidence, the editorial states, suggesting that multifocal soft lenses are comparatively more effective than orthokeratology lenses are for low myopia. In fact, the one direct comparison may indicate the opposite. To keep things simple, she suggests that both work, and eyecare practitioners should pick what lens option best suits their patient. Finally, the editorial states that the chief determinant of myopia progression is age - the sooner you start, the better the overall impact of myopia control will be on final axial length.
|
|
Novel Lens Surface Treatment for GP Lenses |
|
Although applied to scleral lenses, the outcome of this study could have implications for corneal lens surfaces as well:"Assessment of a Novel Lens Surface Treatment for Scleral Lens Wearers With Dry Eye". The investigators compared lens comfort and dry eye symptoms in scleral lens wearers fit with polyethylene glycol (PEG)-based surface-treated scleral lenses and with untreated sclerals. PEG–treated lens wear resulted in significantly improved lens comfort, dry eye symptoms, corneal staining, temporal conjunctival lissamine green staining, lid wiper epitheliopathy, conjunctival papillae, frequency of foggy vision, tear break-up time, and comfortable lens wear time compared with untreated wear. So in dry eye patients, it seems a good option to consider this novel surface treatment, as it could potentially provide improved comfort, reduced symptoms and reduced ocular surface compromise compared with untreated sclerals.
|
|
Lens depositing on rigid gas permeable surfaces can be a frustrating problem for both patients and eyecare providers. Attempts to address depositing usually include changes to patients’ cleaning regimen, lens material, surface treatments, coatings, or even lens fitting properties. While these changes can be helpful, sometimes they aren’t enough to fully eliminate stubborn depositing. While hydrogel lens deposits tend to be more protein-based, (R)GP lens surfaces attract more lipids, with silicone-based lenses even more so compared to (R)GPs containing fluorine. It is logical to think that the hypersecretory forms of meibomian gland dysfunction (MGD) may be more likely to lead to contact lens deposits than the obstructive or hyposecretive forms would, though this remains unconfirmed. Any type of MGD could cause abnormal lipid quality and/or quantity, and practitioners should address this area if (R)GP lens depositing is a persistent issue. In fact, if a hyposecretory form of MGD causes significant tear film instability, deposits may result from an imbalance of tear film components. In conclusion: rather than looking at the (R)GP lens to problem-solve depositing issues, it can be necessary to look at patients and their eyelids instead. With diligent efforts to improve and maintain meibomian gland function, patients will often find that 'clean lids make for clean lenses.'
|
|
Eyelid 'Lift' with Sclerals |
|
One item that has not gotten much attention so far, and that could be a true benefit of scleral lenses over corneal lenses, is when it comes to eyelid issues. Often unmentioned, and maybe even unintentionally forgotten, are those who have lid abnormalities who may benefit from scleral lenses. Karen Lee describes a case of a 54-year-old Caucasian female who presented to the clinic with a moderate ptosis. When questioned about the ptosis, she was against surgical repair and was unaware of sclerals as a possible solution. A quick in-office trial demonstrated dramatic improvement, and the patient was elated. Sclerals designed for ptosis improvement may need increased apical clearance to create a shelf upon which the upper eyelid can rest. This often equates to a thicker tear reservoir, which may be problematic in compromised endothelial cell layers. Close monitoring for signs of corneal hypoxia, such as edema and neovascularization, is indicated. |
|
Interestingly, Melanie Frogozo in 'pediatric and teens contact lens care' column in Contact Lens Spectrum touches on the same possiblity: describing scleral lenses to lift the eyelids as 'a road less travelled'. She describes a case of a 17-year-old Hispanic male with a history of traumatic levator dehiscence of the right eyelid. The patient underwent blepharoplasty surgery at the age of 13 years, with no improvement in cosmetic appearance. A large-diameter 19mm scleral contact lens fitted on the right eye provided the patient with satisfactory improvement in the appearance of his ptosis, while as a 'side effect' his vision was improved by correcting the corneal astigmatism present in that same eye. Hence: scleral lenses can provide cosmetic eyelid elevation and visual rehabilitation and are an alternative treatment modality for patients who would otherwise have to opt for ptosis surgery, with guarded prognosis.
|
|
Amsterdam, Netherlands
Copyright © 2020. All Rights Reserved
This newsletter is kindly supported by:
|
|
|
I-site is an educational newsletter that is distributed on a monthly basis and provides an update on rigid gas permeable-related topics (scientific research, case reports and other publications worldwide). I-site is objective and non-political. Disclosure: I-site's editor Eef van der Worp, optometrist PhD FAAO FBCLA FIACLE FSLS, receives educational grants from a number of industry partners but is not related to any specific company. Please contact us at:
|
|
|
|
|
|
|