Download the OR ACP Newsletter Summer edition PDF here. | |
|
We all deliver care to people who have had long waits for the privilege of a brief conversation with one of us. Or we care for people who landed in the hospital while waiting. In my family network alone, I’ve heard that one of our local health systems has
no new appointments in outpatient internal medicine available until late February, 2025. For another family member getting care in a different local health system, there were no appointments available at all in the time frame they were home between trips out of town. One of my patients was told there are no appointments available for a specialty referral and that they must call back every Monday at 8:00am when appointments are “released” until they can get one scheduled. Frankly, it may be more accurate to say that our healthcare ‘system’ is not friendly to anyone right now as it takes perseverance to navigate the challenges and we all can count ourselves lucky if we already have a primary care physician. However, older patients note important gaps in coordination of their care related to our disjointed system which can influence outcomes.
Once a patient gets to us, we may not have the time or resources to truly address their needs. Mining the medical record for important information from the repeated handoffs, confirming accuracy of the diagnoses and how the plan fits with what matters most to our patient, and having time and energy to connect with the patients and their family on a personal level can really make a difference. Delays in care, repeated transitions between clinicians, and lack of follow up imperil the care we want to provide. Furthermore, longstanding, systemic discriminatory practices against older people and apathy regarding management of their chronic conditions has historically resulted in inferior care for aging adults. The result is that seniors in the United States are sicker than their counterparts in other high-income countries. While great strides have been made in the last fifty years in the care of older adults, excellent geriatric care takes time and resources and providing excellent care to this population of patients can be costly to health systems.
Geriatric medicine and (similarly) the internal medicine physicians and subspecialists who care for older patient populations are in a quiet crisis. With roughly 62 million adults aged 65 and over who now account for 18 percent of the US population - a number that is projected to climb to 84 million by 2054 (23 percent of the population) - this is something we need to figure out.
The most obvious place to start is with a focus on supporting the growth of our professional workforce. (Consider joining Oregon ACP’s delegation at Leadership Day 2025 in Washington D.C.!)
Beyond that monumental issue (which most of us feel at a loss to influence), there are a number of things we do personally or advocate for systemically to make both our own lives better and improve the care we deliver to older patients:
-
Think about the "4Ms". during every visit with an older person. These are the four evidence-based elements of high-quality care - What Matters, Medication, Mentation, and Mobility. We can develop our personal skills and methodically attend to these markers of high-quality care for older adults. Some would add a fifth M (multimorbidity) to this list.
-
Simplify processes to ensure good hand-offs and communication. Insert clear direction for the next steps in the care of a patient discharging from the hospital so the outpatient team knows what is most urgent.
-
Make a commitment to initiating advance care planning discussions; readdress and document decisions as the clinical situation evolves. Document the complexities of advanced care discussions in a visible place in the chart so the expanding clinical team understands what matters most to the patient and family and the life context that informs decisions. These discussions are best done when we focus on our own areas of expertise.
When thinking about practice-level issues, there are changes needed to make this work possible:
- Physicians must have manageable patient panels which account for patient complexity, visit frequency, and time needed for comprehensive care and between-visit work. This is difficult to advocate for in systems where capitated payments incentivize lean resources (including physician time) and where health system leaders sell or promise services without accounting for workforce challenges and the kind of work to be done.
-
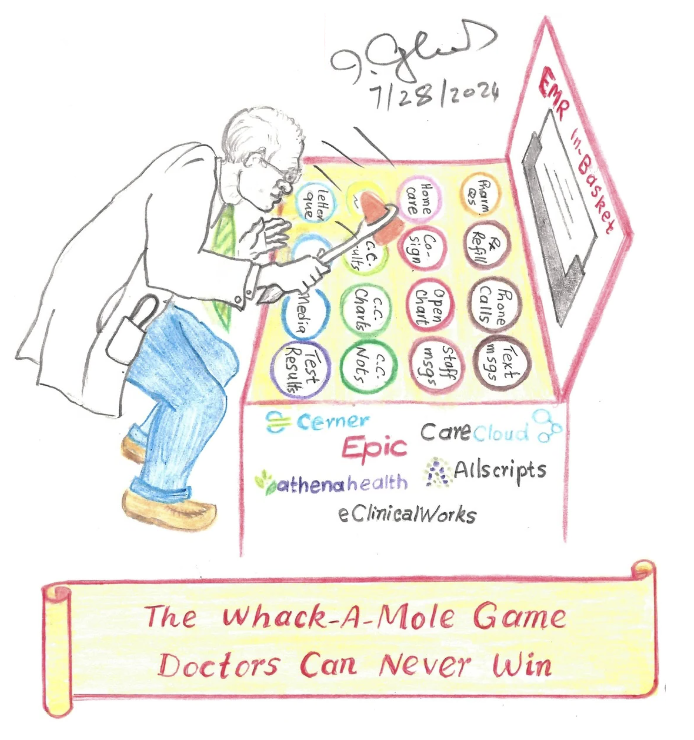
Relief for inbox work must be offered. This work needs to be dealt with in a timely fashion by clinical team members whose skill set allows the issue(s) to be resolved with one touch. If this must be the physician, the time required must be a part of the daily schedule.If a nurse or advanced practice clinician can provide assistance, staffing of teams must account for this work.
-
Schedules should meet the needs of patients and of physicians both. Individualization of scheduling has been lost with the increasing corporatization of healthcare but this can be rolled back if the case is made for the improved efficiency and the benefits to care.
As time-based coding and the G2211 code have rolled out, increased resources should be seen in fee-for-service practices. HMO or capitated practices often follow suit but may lag behind. These resources can be directed in support of the work involved in longitudinal comprehensive care of the complex older patient. That may mean more staff in the office, more time with patients, smaller patient panels, or higher salaries for the physicians providing this care, incentivizing more of us to do this work. With ~75 percent of physicians now employed in large health systems, I’m very curious whether these billing changes will result in changes on the front lines.
| |
|
Please let me know if you are seeing changes or not. I will share this with College leaders so advocacy for resources reflects the realities in Oregon. (Email your ACP governor.)
In the meantime, let’s take care of ourselves, each other, our patients and our families. Enjoy the final days of summer, claim time for yourself before the hustle and bustle begins anew, and be at peace that the work of caring is shared by the community together.
Warm regards,
| |
|
Have you noticed that we are trying to avoid adding to your email deluge? We will push out a “Bulletin” every two weeks on Fridays with important information and opportunities for you to know about. If you miss the Bulletin, the same information will be posted to our website, oregonacp.org, or you can search your email inbox with the word “Bulletin” to pull up the last email. | |
Oregon ACP sent a delegation of seven to Washington D.C. in May this year for Leadership Day 2024. Our newly-minted Dr. Alexander “Mario” Tarasco (class of 2024) and intern Dr. Linh Taylor joined Dr. Lynn Bentson, Dr. Riyad Fares, Dr. Tom Cooney, Dr. Marianne Parshley, and Dr. Jenny Silberger in visits with our Oregon delegation at the Capitol, advocating for the primary care and physician workforce, compensating physicians for the value of care, step therapy, and more. If you are interested in participating in Leadership Day 2025 in Washington D.C., mark your calendar now for April 28th - 29th and plan time for travel.
The local Health and Public Policy Committee have been active in Oregon as well. The committee has been tracking litigation related to Measure 114, which has been tied up in the courts since it was passed by voters in 2022. Oregon ACP joined a coalition representing doctors, nurses, physician associates and others in an evidence-based Amicus Curiae brief, arguing that Measure 114 would improve public safety. Networking and organizational support from Oregon Alliance for Gun Safety was indispensable in this work. If you would like to help sustain their work in this space, you can make a donation to their C3 (tax-deductible) by visiting this link, or their C4 (advocacy and policy work) at this link.
There has also been some preliminary planning started for our next Advocacy Day 2025 in Salem, Oregon, anticipating a focus on workforce issues and issues related to the business of medicine, while not taking our attention completely off the issues of firearm safety and substance use disorder in the state. We will be coordinating our meeting more closely with other physicians advocating in the state. Please plan to join us on March 19th, 2025 in amplifying the voices of our community.
| |
|
Council of Women in Medicine (CWIM)
and Wellness Committee
| |
Join us for the ACP Leadership Luncheon, a family-friendly event on September 28th at Peninsula Park. Come mix and mingle, break bread together, enjoy games and fun activities for all ages. Look for more information on the event in your next Oregon Chapter ACP Bulletin. | |
New Council of Student Members (CSM) | |
|
Please celebrate our new CSM for the Oregon Chapter. The medical students are planning a mentoring luncheon at the Annual Meeting and offering an ongoing mentoring opportunity to Chapter members. If you are interested in connecting with the next generation of physicians planning to go into internal medicine and IM subspecialties, please reach out to office@oregonacp.org.
The students are also helping coordinate a Health Care Equity Fair and Oregon ACP is providing funds to support this initiative. Interested in making a donation to support med students and resident activities? Donate here today!
| |
There is always a need for helping hands to keep the work of the Chapter moving and to grow our reach. Many hands make the work light! Please consider volunteering for one of our committees. | |
|
|
Convocation in Boston at the Internal Medicine Meeting 2024 was well attended by Oregonians. I was joined by Dr. Lori J Farrell, Dr. Xiaoyan Huang, Dr. Mona J McArdle, Dr. Laura P Perry, Dr. Mary Elizabeth Swift-Taylor, Dr. Andrew Felcher, and Dr. Sara Schwanke Khilji at the ceremony, celebrating our shared fellowship in the College. Dr. Marian Hodges was honored on stage as the new MACP from Oregon. I believe everyone was affected by the inspiring speeches given by our then Chair of the Board of Regents, Dr. Eileen Barrett, and our then ACP President, Dr. Omar Atiq.
I usually like to include some quotes in my newsletters so this time I’ve included some quotes from their speeches below. Consider their words and answer the call to action!
Dr. Eileen Barrett:
“Having hope can seem unrealistic or naive. Instead, I like to think of it as knowing that better is possible, and holding onto that truth as both a way finder and a shield. And with the knowledge that hope is both a noun and a verb, I’d like to make 3 asks of you:
First, be relentless in your pursuit of what is right. We know that access to primary care saves lives, that a diverse and inclusive medical profession allows patients to get the best care, that burnout is an occupational phenomenon and not a personal failing, that physicians are often over metriced and under supported, and that physicians give their best care when we have autonomy to do so without undue government interference….
Second, take good care of each other. The challenges are many and they are real…. ‘Just because you’re thirsty, doesn’t mean you can’t be a river for someone else.’ So let’s remember that taking care of each other can help us take better care of patients.
Third, maintain your high standards, despite the milieu of low expectations that surrounds us…. Your high standards can be a beacon or a salve for someone else… Your perseverance and brilliance are inspiring.
| |
|
Your relentlessness, your role modeling, and your high standards have brought you to be recognized…. You are what medicine needs and what the world needs. And with that I will ask you to be that river for someone else….”
Dr. Omar Atiq:
“Our calling represents a promise to those suffering, transcending prejudice, injustice, and intolerance. We honor every life’s inherent dignity and dreams. Our legacy is etched not merely in our medical expertise; rather, it is anchored in our capacity for empathy, our engagement, and our healing touch.
|  | |
We, as physicians, stand witness to the harsh realities of illness and injury. The rise in preventable death and healthcare disparities demand urgent action. It is past time for an affordable, accessible, and efficient healthcare system, not just for those with resources and influence, but for the entire global community. Let us be the voice of conscience, uniting across borders and boundaries, to build a world where the right to life and health is revered, and where the light of compassion illuminates even the darkest corners of despair.
Echoing the timeless words of Hippocrates, “Wherever the art of medicine is loved, there is also a love of humanity." In these challenging times, we find ourselves guardians of a sacred trust: to protect the very essence of life and the inalienable right to health that belongs to every soul. It is a call that demands courage, compassion, and fortitude. The confidence in the collective power of physicians brightens our path; our hands heal, our hearts feel, and our voices speak for the silent.”
| |
Strategic Planning Retreat in March | | |
|
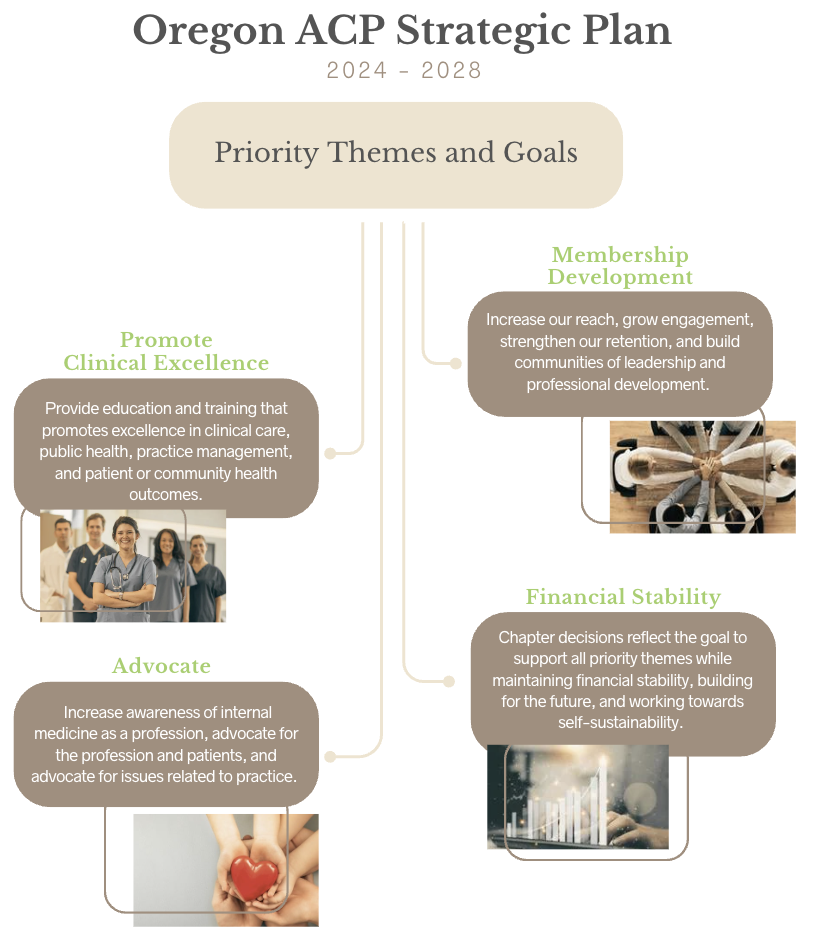
Chapter leaders held a retreat in March to review the current state of our association, the environment in which we are practicing and how that affects our planning, and develop a strategic plan moving forward. Our guiding priorities are outlined in the graphic below. Once final edits have been completed, the strategic plan for 2024-2028 will be posted to our website. | |
The College has a policy recognizing the connection between being engaged voters and health. We encourage our members to counsel patients and colleagues on the health benefits of registering to vote. This is nonpartisan advice and strengthens our democracy, which in turn strengthens the policy that governs the environment in which we deliver care. We all know there are many patients we can’t help through medical care alone.
Please consider making it easy to register to vote! Thanks to Vo+ER, a non-profit nonpartisan association started by an ER physician, you can get resources to make this easier here.
| |
|
We invite chapter members to take part in Story Slam 2024!
Story Slams can be short reflections on a meaningful experience shared with a patient or other life experiences that had a particular impact on our growth as Internal Medicine physicians. Story Slams are often introspective and promote mindfulness in our profession.
Eligibility:
Authors must be Oregon ACP members at the time of submission. All member categories (medical students, residents, members, fellows, masters, and affiliate members) are encouraged to submit.
Awards:
Submissions will be reviewed by the Wellness Committee and selections made to share at the Oregon Chapter Scientific Meeting. Authors will be invited to present their stories on stage at the Scientific Meeting November 14th - 15th in Portland, Oregon.
| |
|
Official Rules for Story Submission:
- Be able to tell your story in 5-7 minutes (about 750-1000 words)
- Do not include any identities of patients or health care professionals in your story
- All stories must be typed in English
- More than one story submission per author is permitted
- Stories that have been previously published elsewhere are not eligible
Presenting:
We will work with the authors to finalize presentation times.
| |
|
Check Out Oregon ACP Members in Action | |
|
American College of Physicians - Oregon Chapter
5727 Baker Way NW, Suite #200 | Gig Harbor, WA 98332
1-877-460-5880
oregonacp.org
Privacy Policy
| |
| | | |