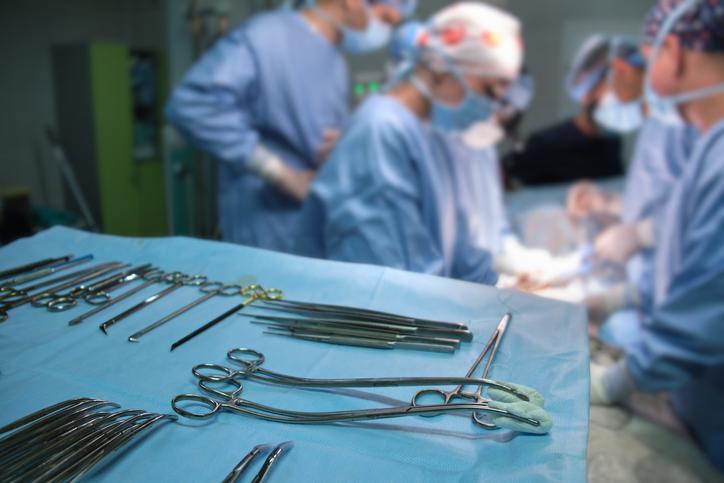
How did your doctor get in the OR?
Physician licensing, credentialing, and privileging
|
|
Doctors are among the most trusted professionals in the United States. Yet, apart from an understanding that they undergo rigorous training in medical school and endure exacting residency programs, few of us appreciate the processes through which our doctors are permitted to care for us in the hospital.
In fact, completion of a medical degree and residency are only the beginning. And a medical license doesn't automatically grant its bearer hospital access.
|
|
The health policy year in review |
|
While 2023 might not have offered any major surprises in healthcare policy, it was not without important developments that are reshaping the healthcare landscape both individually and cumulatively.
Through our original content and our summaries of regulations, legislation, and key events, Applied Policy endeavors to keep our readers abreast of key issues in healthcare policy. As 2023 draws to an end, we want to reflect on and provide updates to some of the more important issues we have considered this year.
In January, we examined the U.S. Pharmacist Shortage. The U.S. Bureau of Labor Statistics predicts that openings for pharmacists will outpace industry growth as a result of the “need to replace workers who transfer to different occupations,” and advocates blame corporate policies for burnout among pharmacists and pharmacy technicians alike. Our story foreshadowed Pharmageddon, a three-day, nationwide walk-out by pharmacists at CVS and Walgreens this fall.
Rite-Aid, the nation’s third largest stand-alone pharmacy chain drugstore, cited labor costs in its bankruptcy filing this year. While pharmacy staffing issues may have contributed, the larger issues were pharmacy benefit managers and the cost of lawsuits associated with the opioid crisis, a topic Applied Policy addressed in our consideration of When Medicine Gets it Wrong in March.
Last week, fallout from the nation’s opioid crisis found its way to the U.S. Supreme Court. On December 4, the justices heard arguments in a case which will determine whether a settlement agreement involving Purdue Pharma, the maker of the prescription painkiller OxyContin, should stand.
In February we considered the future of A New Drug for Alzheimer’s disease, a month after the Food and Drug Administration (FDA) granted accelerated approval for lecanemab-irmb (Leqembi).
The FDA converted Leqembi from an accelerated approval to a traditional approval in July after a determination that a confirmatory trial verified clinical benefit. The Centers for Medicare & Medicaid Services (CMS) announced broader Medicare coverage for the drug the same day. While many patient advocacy groups celebrated the decisions, some observers are asking if Leqembi’s $26,500 list price per patient per year will increase Medicare premiums.
Prior authorization continues to be an issue of concern for healthcare providers and policy makers alike. In the Medical Group Management Association’s Annual Regulatory Burden Survey released last month, nine of out 10 medical practices responding characterized prior authorizations as “very or extremely burdensome.”
Echoing issues considered in our piece on Prior Authorizations and Health Equity, in November CMS, acknowledged that “(p)rior authorization policies and procedures may have a disproportionate impact on underserved populations and may delay or deny access to certain services.” The agency has proposed requiring updates to the composition and responsibilities of Medicare Advantage plan organizations’ Utilization Management Committees that would ensure equity in prior authorization processes.
Prior authorization is also receiving growing attention on Capitol Hill. In October, the Senate Finance Committee launched an investigation into prior authorization practices in Medicaid managed care plans. Last month, 30 House members wrote to CMS urging the agency to increase its oversight of AI or algorithmic software used for coverage determinations by Medicare Advantage plans.
The Inflation Reduction Act of 2022 gave CMS unprecedented authority to negotiate the price of Medicare Drugs. In May, Applied Policy President and CEO Jim Scott moderated the Northern Virginia Health Policy Forum’s discussion of Negotiating Drug Prices: What Should CMS Do Next? in anticipation of the Department of Health and Human Service’s identification of the first ten drugs for the Medicare Drug Price Negotiation Program.
In our July summary of the Hospital Outpatient Prospective Payment (OPP) and Ambulatory Surgical Center (ASC) Payment Systems proposed rule, we noted that CMS continues to solicit public input on the implementation of the No Surprises Act (NSA).
Having previously detailed the challenges of Finetuning the No Surprises Act (NSA), we took note in August when the U.S. District Court for the Eastern District of Texas (District Court) vacated key provisions of the Biden Administration’s regulations for dispute resolution under the NSA in August.
As Insight goes to press, the NSA page of the CMS website notes, “At this time, processing and initiation of batched disputes and single disputes involving air ambulance services remain temporarily suspended.”
While the NSA has been lauded for sparing citizens from personal bankruptcy sometimes associated with medical debt, three private equity firms—Envision Healthcare, American Physician Partners, and the medical helicopter company Air Methods—have blamed it for their own bankruptcies this year.
Finally, although it is tempting to imagine that COVID-19 is in our rearview mirror, the virus and its policy implications linger. One of the defining healthcare issues of 2023 was the end of the public health emergency (PHE) in May, something Applied Policy had anticipated through our summaries of CMS’s webinars.
With the ending of the continuous Medicaid enrollment requirement enacted under the Families First Coronavirus Response Act (FFCRA) and revised through the Consolidated Appropriations Act 2023 (CAA), millions of Americans lost Medicaid coverage. For many, this meant a transition to employer-based health insurance or insurance through the exchanges. For others, it meant the loss of any insurance at all.
According to Georgetown University’s McCourt School of Public Policy, net enrollment in Medicaid has declined by more than 2.8 million children since the end of the PHE. With open enrollment on the exchanges continuing until December 15, it remains to be seen how many Americans will begin 2024 without health insurance.
We will continue to follow all of these topics in 2024, as well as new developments impacting the landscape of healthcare policy.
|
|
Season's Greetings from Applied Policy |
|
The Applied Policy team recently united to participate in a holiday gift drive organized by Volunteer Alexandria. The event afforded us a rare opportunity to put our (previously unrecognized) creative talents to good use in the crafting of homemade wrapping paper and gift tags.
We hope that your holiday season is infused with the same warmth, joy, and heartfelt connections that we shared during this gathering.
|
|
Did we get them right?
Looking back at
NVHPF's predictions for healthcare headlines in 2023
|
|
At the beginning of this year, the Northern Virginia Health Policy Forum hosted leading healthcare reporters for a discussion of what to expect in the industry in 2023.
Applied Policy's President and CEO Jim Scott moderated the conversation with Julie Appleby, Senior Correspondent for Kaiser Health News; Maya Goldman, who covers health policy issues as a reporter for Axios; and John Wilkerson, Washington Correspondent for STAT.
In addition to anticipating CMS's identification of the first 10 drugs for price negotiations under the Inflation Reduction Act, the panelists were closely watching reauthorization of healthcare funding and awaiting the end of the PHE.
Watch highlights of the forum and listen to key predictions below or click here to watch the event in its entirety.
|
|
December 13-14
December 14-15
December 14-15
December 25
Applied Policy office closed for Christmas holiday
January 1
Applied Policy office closed for New Year's holiday
January 11
January 11-12
|
|
Under review/On the docket |
|
Applied Policy is following these rules under review at the Office of Management and Budget:
- Occupational Exposure to COVID-19 in Healthcare Settings
- Interoperability and Prior Authorization for MA Organizations, Medicaid and CHIP Managed Care and State Agencies, FFE QHP Issuers, MIPS Eligible Clinicians, Eligible Hospitals and CAHs (CMS-0057)
- Advance Notice of Methodological Changes for Calendar Year (CY) 2025 for Medicare Advantage (MA) Capitation Rates and Part C and Part D Payment Policies
See all rules under OMB review here.
|
|
FDA News Release
Fierce Biotech
Forbes
MedTech Drive
MedTech Insight
|
|
Insight joke of the month for December |
|
If it is selected for next month’s newsletter,
we’ll send you a package of Piñon Coffee from our source in New Mexico,
Because, like good jokes, good coffee can be a matter of a piñon.
|
|
December podcast recommendation:
Podnosis
|
|
Podnosis from Fierce Healthcare bills itself as “the pulse of the healthcare industry.” And you won't want to miss a beat of the program's engaging weekly discussions of the sector’s hottest topics.
Recent episodes have included an examination of Blue Shield of California's new pharmacy benefits model and a deep dive into the over-the-counter approval of Narcan.
Through interviews with industry experts and in-depth analysis, Podnosis provides insight into what is happening in healthcare today and what we can expect tomorrow.
|
|
|
|
Applied Policy, L.L.C., is a health policy and reimbursement consulting firm strategically located minutes from Washington, D.C.
|
|
|
|
|
|
|