ASIPP 2027–2028
Board Nominations Underway
Nomination Deadline Extended to October 15, 2026
ASIPP is now accepting nominations from active members for its 2027–2028 Board of Directors. Every two years, members elect officers and directors-at-large who will help guide the Society.
Active ASIPP Memers may nominate by clicking this link: https://conta.cc/3U94VUo
Nominations are due no later than October 15, 2026.
Serving on the ASIPP Board is an opportunity to help shape the future of interventional pain management and represent our membership. We encourage nominations from across ASIPP to ensure a strong and diverse group of leaders.
Check your inbox and submit your nominations today!
If you did not receive this e-mail, please notify Karen Avery at kavery@asipp.org.
| | |
Potential risks seen in proposed Schedule I status
for long-available products
| | |
The Department of Veterans Affairs (VA) has announced that precertification is no longer required for Community Care Network (CCN) providers before providing authorized care for Veterans.
The additional prior authorization/precertification requirement has been postponed, and the VA Precertification Portal (VAPP) is being taken offline.
Providers should continue delivering care in accordance with existing VA authorizations and Standard Episodes of Care (SEOCs).
Click here to read the full update from ASIPP.
| | |
According to a research report published in the journal Addiction, researchers analyzing nationally representative data from the 2021–2024 National Survey on Drug Use and Health found that cannabis use among U.S. adults age 65 and older increased from 7.2% in 2021 to 10.5% in 2024.
Among older adults who reported using cannabis during the previous year, an estimated 11.4% met criteria for cannabis use disorder. The researchers said the findings highlight the importance of screening older patients for cannabis use and identifying potential cannabis-related problems before they become more severe.
Click here to read the full article.
| |
The Comments Worked — Partly. What the Final Peripheral Nerve LCDs Give Back, and What They Still Take.
For ASIPP members.
Effective for services on or after October 25, 2026.
| |
Eleven months ago, five Medicare Administrative Contractors proposed to end coverage for nearly every peripheral nerve intervention in chronic pain. Occipital. Stellate ganglion. Suprascapular. Genicular. Pudendal. Posterior tibial. Thoracic. Digital. Ulnar. Three procedures would have survived: radiofrequency neurolysis for trigeminal neuralgia, three lifetime corticosteroid injections for median neuropathy at the wrist, two lifetime injections for Morton’s neuroma. Complex regional pain syndrome was named as investigational.
The finals posted September 10, 2026. They are not what was proposed.
That difference did not happen on its own, and members should understand clearly what produced it. ASIPP filed. So did ASA, AAPM, ASRA, AANA, the Multisociety Pain Workgroup, state medical associations, and eventually the AMA House of Delegates, which adopted a resolution in November 2025 and followed with a formal letter to CMS in December. The contractors read the submissions. We know this because they tell us, section by section, exactly how many systematic reviews, randomized trials, observational studies, and guidelines arrived during the comment period and precisely what each body of evidence changed.
That is the most important thing in these documents, and it is not a coverage criterion. It is a demonstration that a well-evidenced comment campaign moves a multi-jurisdictional LCD.
First, understand what you are actually reading
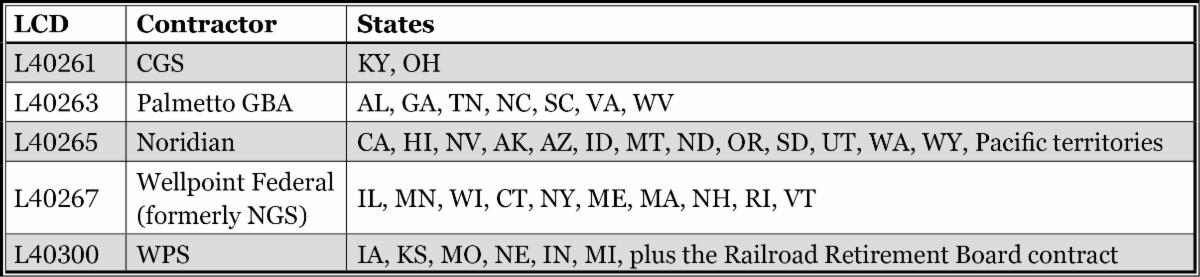
There are five LCD numbers. There is one policy.
| |
Remove the contractor table from the top of each document and the remaining text is identical — not comparable, identical. Same definitions, same twelve-item limitations list, same Kellgren-Lawrence thresholds, same bibliography numbering.
The operational consequence is that a reconsideration request filed with CGS does not move Palmetto, and a favorable ALJ decision in Ohio establishes nothing in Missouri. Future advocacy has to be filed five times or coordinated through the multi-jurisdictional CAC process. Members in the Noridian footprint should confirm L40265’s posting status directly with the contractor; its four siblings are verified, and Noridian participated in the same joint effort, but I have not independently confirmed the final document.
What came back
Sympathetic blocks for CRPS. This is the headline reversal. Stellate ganglion and lumbar sympathetic blocks moved from “investigational” to covered, conditionally. The conditions are demanding and every one of them is a documentation requirement:
-
IASP-criteria diagnosis: continuing pain disproportionate to the inciting event, at least one symptom in three of four categories (sensory, vasomotor, sudomotor/edema, motor/trophic), at least one sign on examination in two of four, and no better explanation
-
CRPS Severity Score documented at baseline, including pain intensity and functional impairment
-
Standard-of-care options tried without improvement, with the treating provider documenting that no alternatives remain
-
Ongoing care by an interdisciplinary or multidisciplinary team addressing psychological effects and functional impairment
For repeat blocks, add ≥50% immediate pain reduction and objective evidence of sympathetic blockade: transient Horner’s syndrome for stellate; for lumbar sympathetic, a ≥2°C rise in the ipsilateral foot or a ≥1.5°C interfoot differential at twenty minutes post-block. Beyond five lifetime blocks, you must document a sustained five-point CSS decrease from baseline lasting three months or longer.
Note how that ceiling was set. Absent any guideline or moderate-quality trial on optimal frequency, the contractors pulled national Medicare claims for 64510 and 64520 from December 2015 through 2025, found 80% of beneficiaries received one to five blocks, and adopted that as the threshold. This is worth flagging in future comments. Utilization is a description of practice, not a measure of medical necessity, and enshrining the observed distribution as a coverage limit converts current practice into a permanent ceiling.
Genicular procedures. Diagnostic genicular nerve injection is covered as the gateway to denervation when all of the following are met: moderate-to-severe OA with pain and disability documented on a validated scale, pain ≥3 months with documented failure of conservative care as tolerated, and radiographic KL grade 3–4. Exclusions: intra-articular injection or knee surgery within three months, inflammatory arthropathy, non-FDA-designated injectates, and high injectate volume — the LCD specifies 0.3–0.5 mL on the rationale that larger volumes destroy prognostic accuracy. Two diagnostic sessions per knee.
Ablation, by radiofrequency or cryoneurolysis, requires ≥50% improvement in pain or function sustained at least three months after the diagnostic injection (difficult to achieve), plus documentation that the patient is a poor surgical candidate or has declined arthroplasty. Two radiofrequency sessions per knee per rolling twelve months.
One documentation trap deserves emphasis: the pain scale must be the same scale at baseline and after each diagnostic procedure. A baseline NRS followed by a post-procedure VAS does not satisfy the criterion. Fix your templates now.
Lifetime caps removed. Median nerve injection converts from a lifetime allowance to a frequency limit: up to three per same median nerve at intervals of no less than two months, individualized to documented response. The Morton’s neuroma lifetime limit was likewise removed.
What did not come back
- Ganglion impar block and denervation: investigational, non-covered, on a very-low-certainty finding across risk of bias, imprecision, indirectness, and inconsistency.
- Therapeutic genicular injection: non-covered — the contractors accepted the nerve as an ablation target while rejecting the block as standalone therapy.
- Genicular ablation after total knee arthroplasty, outside the perioperative period: non-covered.
- The explanation-of-changes section records substantial new literature submitted for occipital, suprascapular, and pudendal nerve blocks but does not record a coverage change for any of them, and the thoracic section states explicitly that no coverage change was made. Members should read sections F through L of their own jurisdiction’s document directly before assuming any of these moved.
- The catch-all survives intact: any therapeutic peripheral nerve injection or denervation not listed as covered is non-covered.
The Bottomline - Pudendal nerve blocks and intercostal nerve blocks: Not Covered.
Two provisions that will generate denials in compliant practices
Anesthesia. Moderate sedation, deep sedation, general anesthesia, and monitored anesthesia care are declared usually unnecessary or rarely indicated for nerve injections, and therefore not reasonable and necessary. Needle phobia and anxiety are addressed by name — the LCD states that oral anxiolytics typically suffice. Exceptions require documentation establishing the need for the specific patient. A standing practice protocol will not survive review.
Image guidance. Ultrasound is covered only where necessary to identify the nerve and visualize needle placement. Fluoroscopy is covered for reasonable and necessary peripheral nerve RFA. Critically, image guidance performed for a non-covered injection is itself non-covered — a denied primary procedure takes the guidance code with it.
Before October 25
-
Pull your jurisdiction’s Billing and Coding Article, not just the LCD. The CPT and ICD-10 detail lives there, and those articles drive the claim edits.
-
Rebuild CRPS and genicular templates around the named criteria — CSS at baseline, temperature differential with time stamp, same pain scale throughout, explicit surgical-candidacy statement. These are not clinical niceties; they are the coverage criteria.
- Decide now which services become patient responsibility and build the ABN workflow before the first denial, not after it.
-
Audit your sedation documentation. If MAC is routine in your practice for nerve injections, that changes October 25.
The unfinished work
The sections that moved, moved because evidence arrived. The sections that did not move — ganglion impar, therapeutic genicular injection, post-arthroplasty ablation, pudendal nerve blocks, intercostal nerve blocks, and the several nerves where new literature was logged but coverage was not changed — did not move because the submitted evidence was judged insufficient in certainty, not because it was ignored.
That is a solvable problem, and it is ours to solve. The reconsideration pathway stays open. What these documents establish is that the contractors will revise a coverage determination when the evidence supports it. What they also establish is the standard: GRADE-appraised, Medicare-applicable, adequately powered, and long enough to matter. Registries, pragmatic trials, and prospective outcome data in the over-65 population are no longer academic exercises. They are the mechanism.
Prepared from the final LCD texts posted to the CMS Medicare Coverage Database, notice period September 10 – October 24, 2026. Verify L40265 (Noridian) status and read sections F–L of your own jurisdiction’s document before relying on any summary, including this one.
| | | SAVE THE DATE - APRIL 15-17, 2027 | | |
Save the date for the American Society of Interventional Pain Physicians' 29th Annual Meeting, April 15 - 17, 2027, in Orlando, Florida.
This flagship educational event will bring together physicians, researchers, and healthcare professionals from across the country for three days of cutting-edge education, collaboration, and professional networking.
Attendees can look forward to our most comprehensive Annual Meeting yet, featuring new educational topics, expanded faculty participation, and innovative program enhancements designed to keep you at the forefront of interventional pain management.
Mark your calendar now and plan to join us in Orlando as we continue advancing excellence in interventional pain management. Additional program details and faculty announcements will be released soon.
Register and book your room today!
| | |
ASIPP is expanding opportunities for Residents and Fellows at the 2027 Annual Meeting, with more ways to present, participate, connect, and represent fellowship programs.
Present Your Research | Connect with Program Directors
Represent Your Program | Programming for Residents & Fellows
Ready to Take Your Place?
Residents and Fellows can submit an abstract to share their research at ASIPP 2027 or apply for a scholarship to help make attending the Annual Meeting possible.
| | |
ASIPP is proud to launch our Resident and Fellow Mentorship Program. This initiative is designed to connect trainees with experienced pain physicians to foster professional growth, provide guidance, and strengthen the future of our specialty.
Each mentor would be paired with one to two trainees, but can take more if interested. Trainees will be responsible for initiating introductions and arranging at least one to two video calls per year. These sessions will provide opportunities for mentees to seek advice on clinical decision-making, career planning, research opportunities, and professional development.
We believe that your experience, expertise, and insight can have a lasting impact on the next generation of pain physicians. By volunteering as a mentor, you will play a critical role in shaping the future of our field and ensuring that ASIPP continues to cultivate excellence in interventional pain medicine.
If you are interested in serving as a mentor, please confirm your participation by filling out the appropriate form below.
| |
ASIPP Submits Comment Letters to CMS on Key CY 2027 Medicare Policies
The American Society of Interventional Pain Physicians (ASIPP) submitted four comment letters to the Centers for Medicare & Medicaid Services (CMS) addressing important policy, payment, and coding issues affecting interventional pain physicians, independent practices, ambulatory surgery centers, and Medicare beneficiaries. The letters address the CY 2027 Physician Fee Schedule proposed rule, the Ambulatory Specialty Model (ASM), proposed changes to ambulatory surgical center payments and neuromodulation procedure reimbursement, and CMS’s Request for Information regarding the Current Procedural Terminology (CPT) coding and valuation process. Across these comments, ASIPP continues to advocate for appropriate reimbursement, preservation of independent practices, continued beneficiary access to non-opioid interventional pain care, and greater transparency and fairness in Medicare payment and coding policies.
Read the full comment letters:
| |
ASIPP is pleased to announce the launch of the Regenerative and Longevity Medicine Section!
This section reflects the growing importance of regenerative and longevity medicine—fields dedicated to restoring health, enhancing vitality, and extending the healthy years of life. From stem cell therapies and tissue engineering to gene therapy and orthobiologics, these disciplines are transforming the way we approach pain management and age-related decline.
Section membership offers:
- Access to ASIPP’s physician database and future data registry
- Opportunities for certification and continuing education
- Section-exclusive resources and updates
No additional cost for ASIPP members!
| | |
Apply now for one of the following 2026 dates:
October 18,
November 14,
& December 12
Four (4) hour virtual exam
- ABIPP Path – Combined CCPM/ CSM Exam
For those with subspecialty in Pain Medicine
Two (2) hour virtual exam
- ABIPP Competency Exam in IPM
For those without primary board certification
Two (2) hour virtual exam
- ABIPP Competency Exam in Regenerative Medicine
Two (2) hour virtual exam
- Controlled Substance Management Competency Exam
Two (2) hour virtual exam
- Documentation, Coding, Compliance, Practice Management Competency Exam
Two (2) hour virtual exam
Questions?
Contact Nik Boulton at nboulton@asipp.org or (270) 554-9412 ext 4208
| | |
Pain Medicine Case Reports (PMCR) and Editor-in-Chief Alaa Abd-Elsayed, MD, PhD would like to invite you to submit case reports and case series to the PMCR journal. Your article will be published free of charge.
Open access journals are freely available online for immediate worldwide open access to the full text of published articles. There is no subscription fee for open access journals. Open access journals are no different from traditional subscription-based journals: they undergo the same peer review and quality control as any other scholarly journal.
Interested in becoming a member of the PMCR Editorial Board?
Editorial board members are asked to review 2-6 manuscripts per year. Please submit your most up-to-date CV to sgold@asipp.org for consideration.
For more information or to submit your articles, click here.
| | |
We are excited to announce that Pain Medicine Case Reports (PMCR) journal (eISSN 2768-5152) has been accepted for inclusion in MEDLINE and PubMed, the prestigious bibliographic database of the U.S. National Library of Medicine. PMCR, a companion publication to the prestigious Pain Physician journal by ASIPP, joins its counterpart in achieving indexing in both MEDLINE and PubMed, marking ASIPP’s dual presence in these renowned databases.
The inclusion of PMCR journal in MEDLINE signifies a higher level of selectivity, as MEDLINE consists of the top 5,200 biomedical journals. This indexing also means that articles from PMCR will be searchable using NLM Medical Subject Headings (MeSH terms) and other metadata.
The selection for MEDLINE follows a rigorous evaluation process by reviewers from the Literature Selection Technical Review Committee (LSTRC). According to their criteria, the scientific quality of a journal’s content is the primary factor considered for indexing.
We extend our congratulations to the Pain Medicine Case Reports Editor-in-Chief, Deputy Editor-in-Chief, Journal Team, and Editorial Board for this achievement, which underscores the significance and excellence of this esteemed journal.
| | | | |
|
Laxmaiah Manchikanti, MD, Mahendra R. Sanapati, MD, Vidyasagar Pampati, MSc, Ramarao Pasupuleti, MD, Alexander Bautista, MD, Amol Soin, MD, Annu Navani, MD, Alan D. Kaye, MD, PhD, Rajesh Naidu Janapala, MD, Mayank Gupta, MD, Alaa A. Abd-Elsayed, MD, and Joshua A. Hirsch, MD
| | |
Laxmaiah Manchikanti, MD, Mahendra R. Sanapati, MD, Vidyasagar Pampati, MSc, Allen Dennis, MD, Kenneth D. Candido, MD, Alan D. Kaye, MD, PhD, and Joshua A. Hirsch, MD
| | |
Laxmaiah Manchikanti, MD, Sheri L. Albers, DO, Vidyasagar Pampati, MSc, and Mahendra R. Sanapati, MD
| | |
Laxmaiah Manchikanti, MD, Emilija Knezevic, none, Nebojsa Nick Knezevic, MD, PhD, Rajesh Naidu Janapala, MD, Mahendra R. Sanapati, MD, Alexander Bautista, MD, Vidyasagar Pampati, MSc, Alan D. Kaye, MD, PhD, Amol Soin, MD, Alaa A. Abd-Elsayed, MD, Mittal Prajapati, MD, and Joshua A. Hirsch, MD
| | | | |